



Aging parent at home
Missed meals, forgotten medications, daily tasks becoming harder. A caregiver brings the right support — without taking away independence.
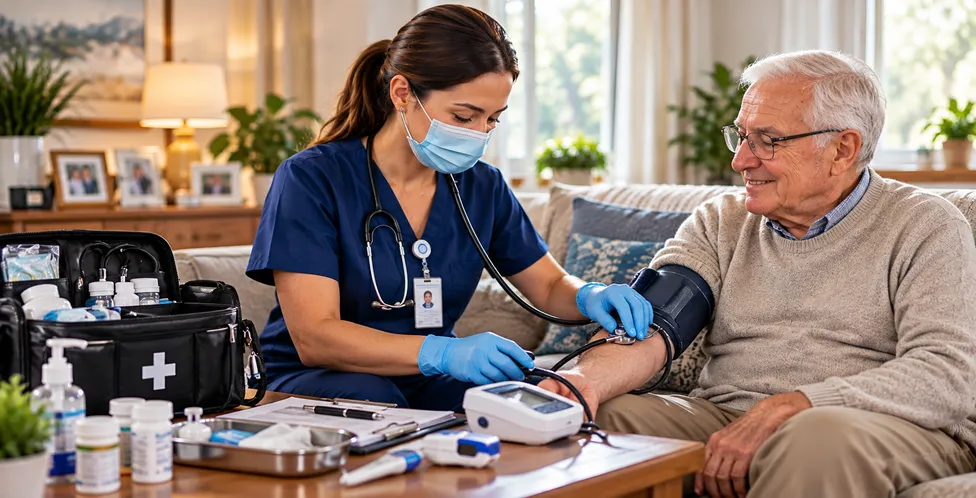
In-person dose reminders, a daily medication log, and refills caught early, always following what the doctor prescribed.
4.9 (250+ Reviews)


98% Client satisfaction
There is usually a shelf. Eleven bottles, two of them from the same drug under different names, one that ran out in March, and a blister pack from a specialist nobody has told the family doctor about. Somewhere in there is a schedule that made sense when it was written down.
Most families discover the problem sideways. A dose gets taken twice because the first one was forgotten. A prescription runs out on a Friday. Someone quietly stops taking the expensive one. None of it looks like a crisis until the day it does.
Medication management at home from Good Hands Home Health Care is the practical side of the problem: a caregiver who is there at the right times, keeps the schedule visible, notices what has been missed, and keeps the supply from running out. A caregiver does not decide what anybody takes — and this page is clear about where that line sits.


When you need care day and night, we're there!




From aging at home to recovery and long-term conditions, every family's situation is different. We listen first, then build care that fits.
Missed meals, forgotten medications, daily tasks becoming harder. A caregiver brings the right support — without taking away independence.


Healing at home shouldn't feel overwhelming. Hands-on help with mobility, routines, and daily care makes the return smoother for everyone.


Chronic illness or memory changes don't have to mean leaving home. Consistent in-home support keeps comfort, dignity, and connection close.


The work is unglamorous and mostly about consistency. Visits are timed to the doses that matter most, rather than to whatever slot was convenient.
Reminders in Person — the caregiver stays until the dose is actually taken, rather than put down and forgotten.
A Daily Written Record — what was taken and when, kept up every day and shared with the family.
Supply & Collections — prescription pick-ups and an eye on what is running low, before the Friday it runs out.
Practical Help — bringing the container, reading the label where eyesight is the problem, opening packaging where hands are, water and food where the instructions call for them.
Watching & Reporting — drowsiness that was not there last week, a rash, nausea, a change in balance — reported to the family and, where authorised, to the practice or home health agency involved.
Where the schedule includes time-critical doses, the care plan is built around those times specifically.
Good Hands Home Health Care has served Pennsylvania families for more than eight years and holds accreditation from the Accreditation Commission for Health Care, alongside membership in the Pennsylvania Homecare Association.
Every one of our 120-plus caregivers clears a rigorous screening process before entering a client’s home, including a criminal background investigation and a psychological evaluation.
Who Benefits from Medication Support
Seniors with a schedule that has grown — several medications, several times a day, from several prescribers.
People just home from hospital, when prescriptions change all at once and the risk is highest.
Households living with memory changes, where the question is no longer wanting to take it but remembering that they already have.
Adult children living far away who need to know what is genuinely being taken, not the Sunday-phone-call version.
Behind each caregiver stands a team that supervises the care, revises the plan as prescriptions change, and provides backup coverage when a caregiver cannot make a shift. A schedule that depends on somebody being there at eight in the morning needs to hold on the mornings that somebody is ill.


Our experienced team handles every detail—from the initial consultation to ongoing support—so your family can focus on what matters most.

You tell us what the schedule looks like and where it is breaking down. We confirm availability.
Our team visits the home, goes through the current schedule and the shelf it lives on, and confirms exactly which tasks are within scope for your household. The visit schedule and the quote are settled here.
We select a caregiver suited to the needs, the schedule and the personality involved — for households living with memory changes, an approach that does not turn every dose into a negotiation is the deciding criterion.
Care begins under supervision, with the plan revised as prescriptions change and backup coverage arranged whenever a caregiver is unavailable.







630 Freedom Business Center Dr., 3rd Floor
King of Prussia, PA 19406
Phone Number: 610-285-1095
info@goodhandshomecarellc.com
Mon - Fri: 9AM to 5PM EST
Sat - Sun: On-Call Only
Families across Pennsylvania trust us with the care of the people they love most. Read real reviews from our clients, their families, and the caregivers who make our home health care possible.

Great home care agency. I highly recommend it.


Great service.

Great place to work. I highly recommend it.

Very professional and friendly home care agency. Great place to work. I would recommend this company.
Every member of our team is carefully selected, professionally trained, and committed to providing dependable, respectful care that helps your loved ones feel safe, comfortable, and supported every day.





We're proud to provide trusted in-home care across 14 Pennsylvania counties. Whether you're visiting our office or looking for a home nurse near you, our team is here to help every step of the way.
630 Freedom Business Center Dr., 3rd Floor
King of Prussia, PA 19406
Phone Number: 610-285-1095
info@goodhandshomecarellc.com
Mon - Fri: 9AM to 5PM EST
Sat - Sun: On-Call Only
In home care it means the practical support that keeps a prescribed schedule on track: reminders at the right times, a written record of what was taken, prescription collections, watching supply levels, and reporting missed doses or changes to the family. Deciding what a person takes is clinical work carried out by a physician or pharmacist and is a separate thing.
Non-medical caregivers typically remind, bring the container, open packaging and stay present until the dose is taken, rather than administering medication. Where the boundary sits precisely depends on state regulation and on the individual agency, so it is worth asking any provider directly. We confirm exactly what applies to your household during the assessment visit.
A reminder prompts and supports the person, who takes the medication themselves. Administration means someone else gives it to them, which is a clinical task performed by licensed staff. The distinction matters because it determines which service a household needs, and the two often run alongside each other.
Filling or sorting a pill organiser is a licensed task in many places rather than something a non-medical caregiver does. Households commonly have this handled by a pharmacy, by a home health nurse or by a family member, with the caregiver then bringing the organiser at the right times. This is one of the specifics we confirm at the assessment.
Medicare does not pay for non-medical care at home. It may cover home health care ordered by a physician, and Medicare drug plans separately include medication review programmes for people who qualify, which is a pharmacist service. The daily support described here is usually funded privately, through long-term care insurance, through VA benefits, or through Pennsylvania’s Medicaid programs where the person qualifies.
The caregiver records it and reports it to the family, and where authorised, to the practice or home health agency involved. What should be done about a missed dose is a clinical question, so the caregiver reports rather than decides. The value of a daily record is that a pattern of missed doses gets noticed in days instead of months.
Yes. Collections and keeping an eye on what is running low are part of the visit, and running out on a Friday afternoon is one of the more common ways a schedule breaks down. Arrangements with the pharmacy are agreed with the family when care starts.
Yes. Where doses fall at times far apart, several shorter visits often work better than one long one, and the schedule is built around the times that matter rather than around a standard slot. Where doses fall overnight, that usually points toward overnight coverage instead.



The term covers two different things, and mixing them up is the reason families end up with the wrong kind of help.
Clinical medication management means reviewing what a person takes and deciding whether it is right: checking for interactions, adjusting doses, stopping what is no longer needed. That is the work of a physician or a pharmacist, and it happens in a consultation rather than in a kitchen.
Medication management at home means everything that has to happen for the plan to actually get followed. Being there at the right times, keeping the schedule visible, noticing when something has been missed, keeping the supply from running out, and making sure the family and the medical team know what is genuinely being taken rather than what is on the prescription.
This page is about the second one. A caregiver does not decide what anybody takes.
This is the first question almost every family asks, and it is worth answering plainly before anything else. Non-medical home care and clinical home health care are separate services with separate rules, and the boundary is drawn by state regulation and by each agency’s own licence rather than by preference.
| Typically Within Scope for a Non-Medical Caregiver | Typically Outside the Scope of Non-Medical Care |
|---|---|
| Reminding the person that it is time to take something | Deciding what a person should take, or changing a dose |
| Bringing the container or the pill organiser to them | Injections, infusions and anything requiring clinical technique |
| Reading the label out loud where eyesight is the problem, opening packaging where hands are the problem | Advising on interactions or on whether a medication is still needed |
| Staying present so the dose is actually taken, and recording that the reminder happened | Filling or sorting a pill organiser, which in many places is a licensed task |
| Collecting prescriptions, watching supply levels, reporting missed doses and side effects to the family |
Where the boundary sits precisely depends on the state and on the agency, and that is a question worth asking any provider directly rather than assuming. We go through exactly what applies to your household during the assessment visit, so the care plan reflects it rather than glossing over it.
Where a household needs tasks in the second column, they fall to home health care ordered by a physician, which runs alongside daily support rather than instead of it.
Schedules rarely fail because someone is careless. They fail for reasons that are structural, and knowing which one applies decides what kind of help works.
Almost every household that runs into trouble has the same underlying problem: there is no single accurate list of what the person actually takes. There is a prescription record at one practice, a different one at another, a bag of bottles at home, and an over-the-counter habit nobody has mentioned to anyone.
A caregiver in the house daily is well placed to keep that list current, because they see what is genuinely being taken rather than what was prescribed. The list goes to appointments with the person, which changes the quality of the conversation with the doctor considerably.
Over-the-counter products, supplements and anything bought at the pharmacy without a prescription belong on it too. Families routinely leave those off, and they are exactly what a physician needs to know about.
The days after discharge carry more medication risk than any other stretch. Several things change at once, the old routine no longer applies, and the person is tired, sore and least able to hold a new system in their head.
Support here is concentrated and short: getting the new schedule written up in a form the household can actually use, making sure the first days follow it, checking that what was stopped has genuinely stopped, and confirming that everything newly prescribed has been collected. Our post-surgery and hospital-to-home page covers the wider picture of that first week.
Where the schedule includes doses that are time-critical, the care plan is built around those times specifically. On our Parkinson’s care page there is more on how that reshapes an entire day.
Cognitive changes turn this from an organisational problem into a supervision problem, and the two need different answers.
Someone may take a dose and have no memory of it twenty minutes later, then take it again. Someone may be certain they have taken it when they have not. Pills get moved, put somewhere safe, or refused because the person does not recognise them. Arguing about it does not work and damages the relationship the caregiver needs.
What works is presence at the right times, a routine that stays identical day to day, an approach that does not turn every dose into a negotiation, and accurate reporting to the family so the medical team knows what is actually happening.
For an adult child an hour away or in another state, the value here is visibility. A caregiver in the house sees the pattern over weeks rather than the version reported during a Sunday phone call.
That means the family finds out that the evening dose has been missed four times this month, that a new prescription has not been collected, that the supply runs out on Thursday, or that something has changed since the medication was adjusted. All of it is easy to catch daily and nearly impossible to reconstruct afterwards.
Medication support is not billed separately. It sits inside the hourly care visit, so what drives the cost is how many visits a week the schedule needs and at what times.
Where doses fall at times far apart, a household may need several short visits a day rather than one long one, and that shapes the schedule more than anything else. What moves the hourly rate is the level of support required, the number of hours booked, and whether coverage falls on weekdays, weekends, evenings or overnight.
The rate covers the caregiver’s time, the supervision behind them, the written care plan and backup coverage. There is no separate charge for the assessment visit or for building the plan.
Medicare does not pay for non-medical care at home. It may cover home health care ordered by a physician, and separately, Medicare drug plans include medication review programmes for people who qualify, which is a pharmacist service rather than a caregiving one. Families commonly fund daily support through private pay, long-term care insurance, VA benefits where the person is eligible, or Pennsylvania’s Medicaid Waiver and Community HealthChoices programs where they qualify.
To get an exact figure, schedule the free in-home assessment. You will leave that visit with a written scope and a rate, with no obligation attached.
Medication support is part of a wider visit rather than a service booked on its own.